
Patient information
Skin cancer
Skin cancer is the most common type of cancer in Denmark. Here you can read what skin cancer is, what it looks like, when to see a doctor, and how it is detected and treated.

Medically reviewed by Martin Glud, consultant and specialist in dermatology, PhD
Updated 9 November 2026
Look out for
Sores that don't heal
Especially on the face – or a lump that bleeds or weeps.
Red, scaly patches
Changes in the skin that don't go away.
A pearly lump
A shiny, slightly translucent lump, usually on the face.
Introduction
What is skin cancer?
Skin cancer develops when cells in the skin are damaged – most often by UV radiation from the sun or sunbeds – and start to divide uncontrollably. That is why skin cancer most often appears where the skin has had the most sun: the face, ears, scalp, neck and hands.
A distinction is made between non-melanoma skin cancer – basal cell carcinoma and squamous cell carcinoma – and melanoma (malignant melanoma), which is less common but more serious. Actinic keratosis is a precursor that can develop into squamous cell carcinoma.
-
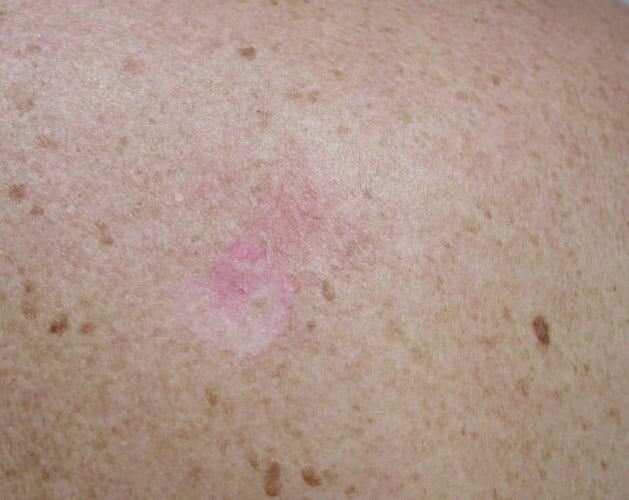 Basal cell carcinoma
-
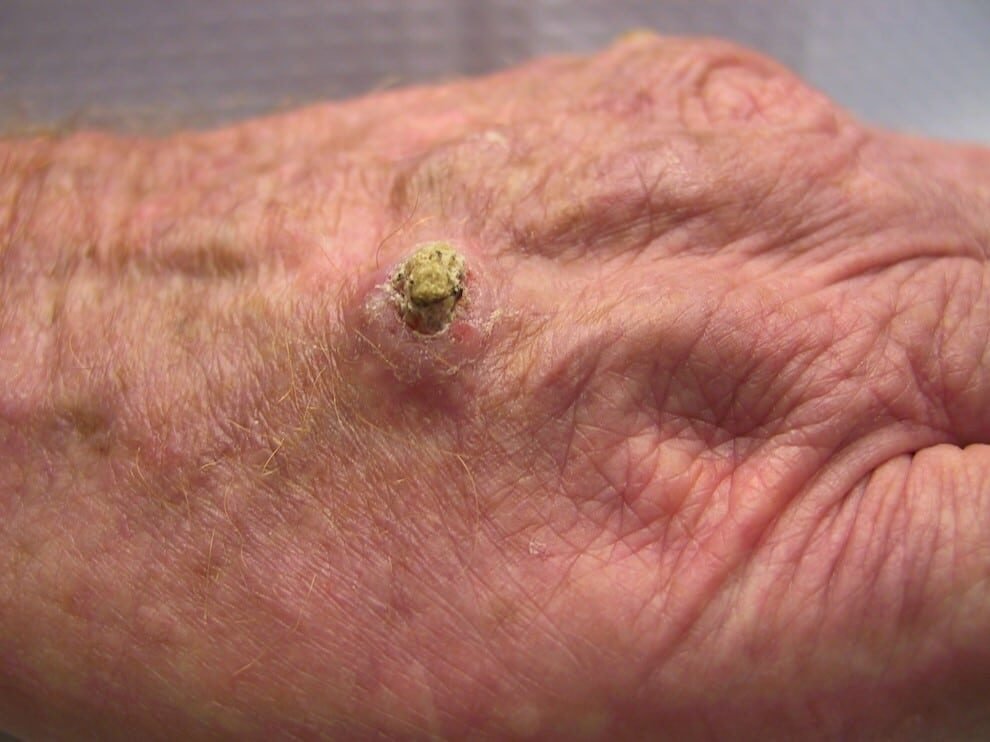 Squamous cell carcinoma
-
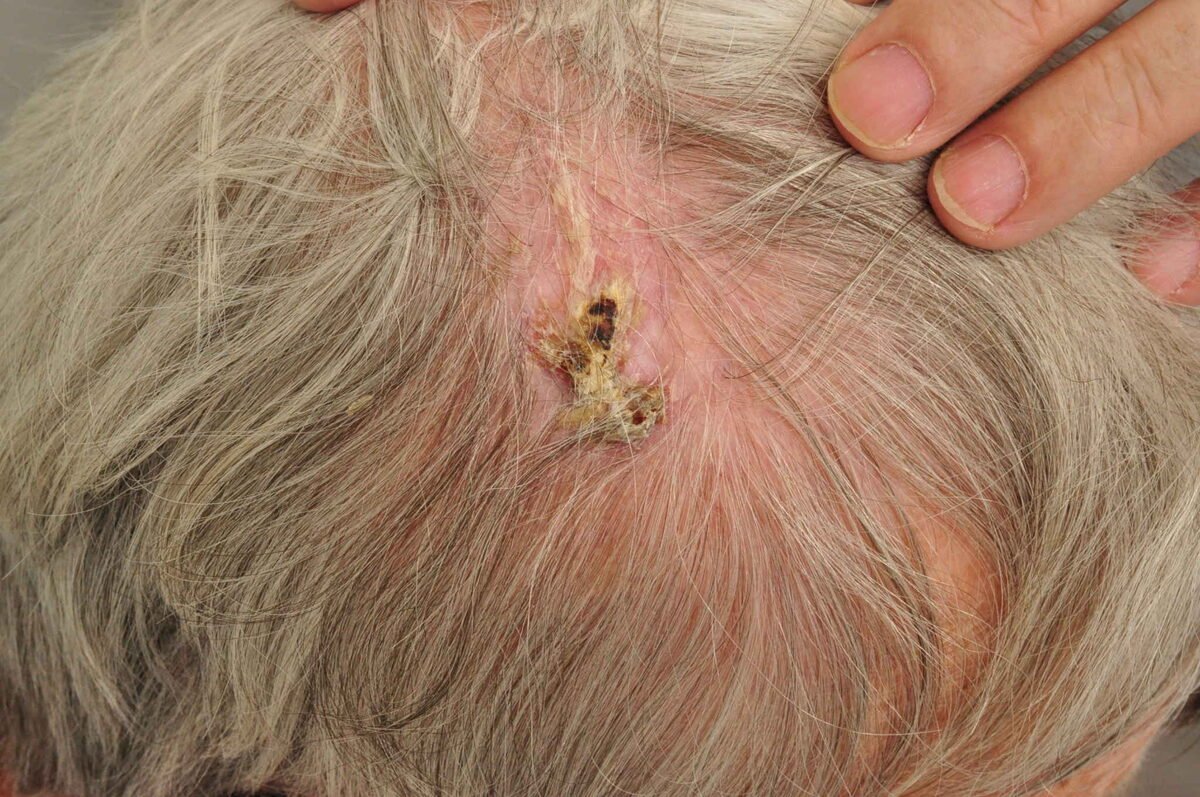 Actinic keratosis
-
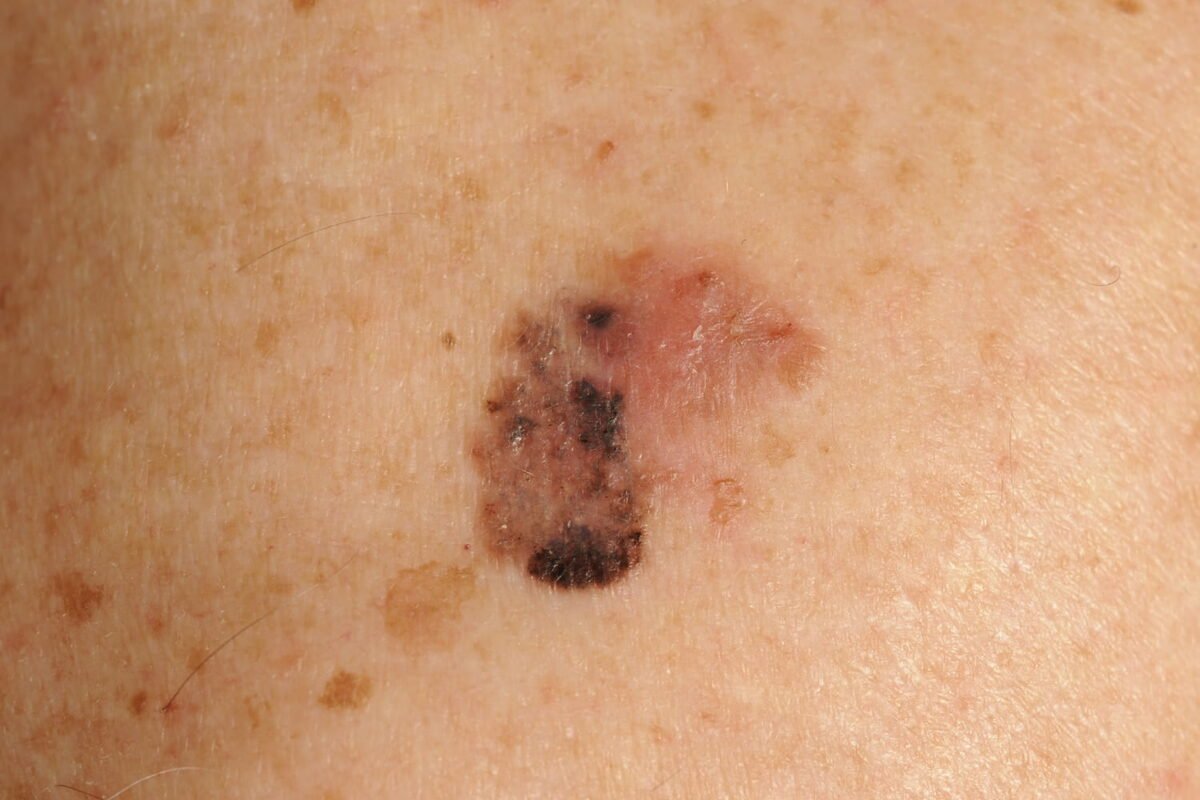 Melanoma
Read more about skin cancer where it most often appears: skin cancer of the scalp and skin cancer on the face, ear and lip.
See the different types of skin cancerSymptoms
What skin cancer can look like
Non-melanoma skin cancer can appear anywhere on the body, but the vast majority of cases are on the head and neck. Often it is a sore that won't heal, or a lump that bleeds or weeps. An experienced dermatologist will usually recognise skin cancer easily, but it can be mistaken for a harmless skin condition.
Nodular basal cell carcinoma
The most common form. It usually appears on the face as a pearly lump, sometimes with a sore.
Superficial basal cell carcinoma
Usually seen on the body, especially the upper arms, as red, scaly changes in the skin. It can be mistaken for eczema or psoriasis, so it is important to have a dermatologist look at the area.
Infiltrative basal cell carcinoma
A less common form with a more aggressive growth pattern and a higher risk of recurrence. It looks like scar tissue, and it can be hard to see where the cancer ends and the healthy tissue begins.
Precursor: actinic keratosis
Small red or brownish patches that may be scaly or feel rough, on skin that has had a lot of sun over the years. Actinic keratosis is not cancer, but it needs treatment because it can develop into squamous cell carcinoma.
Non-melanoma skin cancer is not melanoma
It is important to distinguish between non-melanoma skin cancer and melanoma (malignant melanoma). The two diseases behave differently and are treated differently.
Incidence
The most common form of cancer in Denmark
Basal cell carcinoma is the most common form of skin cancer, and the number of new cases is still rising. According to the Danish Cancer Society (Kræftens Bekæmpelse), there were 12,000 new cases in 2014, evenly split between men and women – a doubling in ten years.
Skin cancer grows slowly. It most often appears on the face, ears, back of the neck and upper chest, but it can occur anywhere on the body. The disease mainly affects older people, but in recent years it has become more common among younger people.
- 30%
- lifetime risk of developing skin cancer.
- 20%
- of all new cases occur in people under the age of 50.
- 40%
- risk of new skin cancer elsewhere on the body if you have had it once.
- Over the past 30 years, the number of cases of skin cancer has tripled among Danish women and more than doubled among Danish men.
- Around 40 people in Denmark are diagnosed with skin cancer every day – more than a whole school class. That is more than 14,600 new cases a year.
- More than 121,000 people in Denmark have been treated for the disease. The real figure is probably twice as high, as many cases are not registered.
Risk factors
Who is at risk?
The risk of skin cancer increases with age and with how much sun you have had – both outdoors and in sunbeds. That is why skin cancer mainly appears on the areas that get the most sun.
- Fair skin that burns easily in the sun
- Previous radiotherapy
- Intake of arsenic (formerly used to treat psoriasis)
- Long-term contact with carcinogenic substances such as soot and tar
- A weakened immune system or treatment with immunosuppressive medication – in these cases skin cancer appears to develop 10–15 years earlier than normal
If you have been diagnosed with skin cancer once, there is a 40% risk that you will get it again somewhere else on your body. That is why we recommend a yearly check-up with a dermatologist. A full-body skin check is a good way to keep an eye on all of your skin.
How to protect yourself
You can lower your risk by protecting your skin from the sun: seek shade between 12:00 and 15:00, wear clothes and a sun hat, and use sunscreen where your skin is not covered. Avoid sunbeds. Read more from the Danish Cancer Society (Kræftens Bekæmpelse) about UV radiation and cancer.
See a doctor
When should you see a doctor?
Have a doctor look at your skin if you have:
- a sore that does not heal, or that bleeds again and again
- a lump or patch that grows or changes
- a red, scaly patch that does not go away
- a mole that changes in size, shape or colour, or that stands out from the others
Don't wait to see whether it goes away on its own. The earlier skin cancer is found, the easier it is to treat. You can see your GP – or book an appointment directly with one of our specialists, without a referral.
Book an appointmentDiagnosis and treatment
How the diagnosis is made
The diagnosis is made from a tissue sample, either a biopsy or a scraping (curettage).
Skin cancer destroys the tissue where it grows, but only very rarely spreads to other parts of the body. On the other hand, there is a considerable risk that it will come back after treatment – half of all recurrences are seen within the first three years. The risk depends on the cancer's size, type and location, on the treatment and on the doctor's experience.
Skin cancer can be treated in several ways: curettage and creams, which are used mainly for low-risk tumours; surgery such as Mohs surgery; and radiotherapy.
Mohs surgery gives the greatest certainty that all of the cancer has been removed, and therefore the lowest risk of recurrence. Five years after treatment, the recurrence rate is 1–3% for skin cancer that has not been treated before, and 5–10% for skin cancer that has come back. Mohs surgery is therefore regarded as the gold standard for high-risk basal cell carcinoma on the head and neck, because the method gives the safest and best cosmetic result.
Many people get skin cancer on the ears, nose and around the eyes, where a scar can be bothersome. Because Mohs surgery removes only the tissue that is necessary, the scar is kept as small as possible.
Read also about basal cell carcinoma and squamous cell carcinoma in the Danish Patient Handbook on sundhed.dk, and about non-melanoma skin cancer from the Danish Cancer Society (Kræftens Bekæmpelse).
Sources
- The Danish Cancer Registry (Cancerregistret) 2014. www.sundhedsdatastyrelsen.dk (10 April 2016).
- Miller DL, Weinstock MA. Nonmelanoma skin cancer in the United States: incidence. J Am Acad Dermatol 1994;30:774-8.
- Leman J, McHenry P. Basal cell carcinoma. Arch Dermatol 2001;137:1239-40.
- Diffey BL, Langtry JAA. Skin cancer incidence and the aging population. Br J Dermatol 2005;153:679-80.
- Birch-Johansen F, Jensen A, Mortensen L et al. Trends in the incidence of nonmelanoma skin cancer in Denmark 1978-2007: rapid incidence increase among young Danish women. Int J Cancer 2010;127:2190-8.
- Baxter JM, Patel AN, Varma S. Facial basal cell carcinoma. BMJ 2012;345:e5342.
- Rowe D, Carroll R, Day C. Long-term recurrence rates in previously untreated (primary) basal cell carcinoma: implications for patient follow-up. J Dermatol Surg Oncol 1989;15:315-28.
- Smeets NWJ, Kuijpers DIM, Nelemans P et al. Mohs’ micrographic surgery for treatment of basal cell carcinoma of the face – results of a retrospective study and review of the literature. Br J Dermatol 2004;151:141-7.
Questions and answers
Good to know about skin cancer
What are the symptoms of skin cancer?
Look out for sores on the skin that don't heal – especially on the face – red, scaly changes that don't go away, and pearly lumps. Non-melanoma skin cancer can develop anywhere on the body, but most cases are on the head and neck. It is often a sore that won't heal, or a lump that bleeds or oozes. See the different types of skin cancer.
How is skin cancer diagnosed?
The diagnosis is made from a tissue sample – either a biopsy or a scraping (curettage). If the sample shows skin cancer, the doctor goes through your treatment options with you. Scraping and creams are mainly used for low-risk tumours, while Mohs surgery gives the greatest certainty that all of the cancer has been removed, and therefore the lowest risk of recurrence.
Read more about skin cancer
-
Types of skin cancer
Basal cell carcinoma, squamous cell carcinoma, actinic keratosis and melanoma – with pictures.
Read more -
Skin cancer of the scalp
Sores that won't heal, and how Mohs surgery preserves as much hair as possible.
Read more -
Skin cancer on the face, ear and lip
Symptoms, prevention and treatment in the places where skin cancer most often develops.
Read more
Private clinic
Unsure about a spot?
As a private clinic, we can offer short waiting times, and you don't need a referral. A specialist can look at a single spot or examine all of your skin.